


how do i choose a ups system for a hospital? | Insights by ShanPu

Quick Answer
To choose a UPS for a hospital, first separate life-safety, clinical, IT, and noncritical loads, then size from measured kW/kVA, starting currents, required autonomy, and redundancy. ShanPu can discuss online, rack-mounted, or modular UPS options and related service support. Final selection depends on the electrical design, applicable healthcare requirements, battery conditions, testing, and site conditions.
How ShanPu Supports how do i choose a ups system for a hospital? Projects
ShanPu supplies standby, online, rack-mounted, and modular UPS products for power-system applications. For a hospital project, its pre-sales and technical discussions can help relate product choices to the stated load profile, operating mode, battery arrangement, and installation constraints; the applicable option remains subject to engineering review.
ShanPu lists ISO9001, ISO14001, OHSMS18001, CE, and RoHS certifications across its quality, environmental, safety, and product compliance framework. Buyers should confirm input and output voltage, phase configuration, kVA, kW, power factor, autonomy, bypass, communications, redundancy, and battery type; MOQ, lead time, testing scope, and quotation must be confirmed per project through the company’s 1+3 service model.
Request Hospital UPS Specifications and Project Pricing
Please provide the critical-load schedule, measured kW and kVA, voltage and phase requirements, required autonomy, generator details, redundancy preference, installation environment, and target quantity. These details support discussion of suitable UPS architectures, battery configurations, testing steps, and quotation conditions. Project inquiries can be directed through www.gdshanpu.com or SPU@gdshanpu.com.
Hospital UPS Selection FAQs
How do I calculate hospital UPS capacity for critical loads?
Begin with a circuit-level inventory that distinguishes life-safety, clinical, information technology, communications, and noncritical equipment. Record both real power in kW and apparent power in kVA because the UPS inverter and upstream conductors must accommodate both values. Include simultaneous demand, equipment power-factor behavior, nonlinear current, inrush or starting current, and any operating mode that creates a higher load than normal use. A design margin may be appropriate, but it should be based on documented expansion plans rather than an arbitrary percentage. Check the proposed rating against generator capacity, short-circuit coordination, thermal conditions, and the manufacturer’s overload curve. Hospital electrical engineers should also verify the calculation against the essential electrical system and applicable local requirements before procurement.
Should a hospital use online or modular UPS architecture?
An online double-conversion UPS is often considered when sensitive clinical, communications, or data-processing loads require regulated output and controlled transfer behavior. A modular UPS can provide capacity scaling and module-level service flexibility, but its suitability depends on the power modules, static bypass, maintenance bypass, controls, battery arrangement, and common-bus design. Modularity does not automatically create redundancy; the engineering design must determine whether a failed module leaves adequate capacity for the connected load. Compare efficiency across the expected load range, harmonic performance, generator compatibility, fault-clearing behavior, service access, and the consequences of bypass operation. The correct architecture is therefore a system-level decision, not simply a choice between two product labels.
What battery runtime does a hospital operating room require?
There is no universal operating-room runtime because autonomy is determined by the hospital’s essential-power strategy, generator start and stabilization sequence, orderly-shutdown policy, and applicable electrical regulations. The UPS battery must support the defined load for the specified period at the actual end-of-discharge voltage, not merely at a nominal rating. The calculation should include battery aging assumptions, ambient temperature, recharge capability, discharge rate, inverter efficiency, and possible future load changes. Confirm whether the operating room is connected to a safety service, essential service, or another locally defined category; those classifications affect the power architecture. Runtime should be validated through documented calculations and commissioning tests coordinated with the facility’s electrical and clinical stakeholders.
Which hospital circuits need separate UPS protection and bypass?
A hospital should not place every receptacle or building load on one UPS output. Circuit selection normally follows the facility’s essential electrical system design, medical-location classification, life-safety strategy, clinical risk assessment, and local code requirements. Critical loads may include selected medical equipment, communications, monitoring, controls, and information systems, while motors, heating loads, imaging systems, and other high-demand equipment may require separate analysis. A maintenance bypass can preserve supply during planned UPS work, but it also changes the protection and power-conditioning path; its rating, interlocking, switching sequence, and fault coordination require careful review. Standards such as IEC 60364-7-710 address electrical installations in medical locations, but the adopted jurisdictional rules and hospital engineering documentation control the final circuit arrangement.
How do I verify UPS compatibility with medical equipment?
Request electrical input and output data for every important load, including nominal voltage, frequency, phase, kW, kVA, power factor, crest factor, inrush current, leakage-current constraints, and acceptable voltage or frequency limits. Verify the UPS output waveform, harmonic performance, neutral configuration, grounding arrangement, electromagnetic compatibility, and behavior during transfer or bypass. Equipment with rectifiers, variable-speed drives, compressors, or imaging functions may interact differently with the UPS and standby generator than ordinary IT loads. Confirm alarm interfaces, communications protocols, isolation requirements, and manufacturer restrictions for each clinical device. Compatibility should be demonstrated through engineering documentation and, where risk justifies it, a witnessed test using representative equipment or an approved load bank rather than inferred from the UPS nameplate alone.
What maintenance and redundancy plan should hospital UPS include?
The plan should address the UPS topology, available capacity during a module or component failure, maintenance bypass, battery strings, ventilation, alarms, communications, spare parts, and recovery procedures. N+1 capacity is a design approach, not a substitute for reviewing common points of failure such as a shared static bypass, switchgear, control network, or battery system. Facilities should define inspection intervals, battery impedance or conductance checks where appropriate, functional transfer tests, discharge or load tests, firmware and event-log management, and documentation of corrective actions. Dual-cord equipment may require separate UPS paths or a suitable transfer system, while single-cord loads need a different risk assessment. Maintenance procedures must be coordinated with clinical operations so testing does not unintentionally interrupt protected equipment.
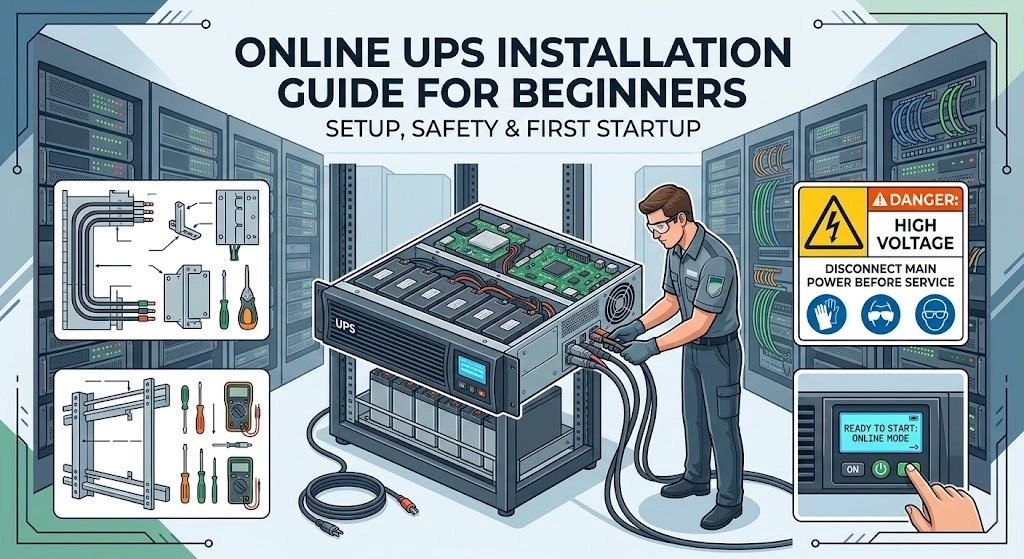
Online UPS Installation Guide for Beginners: Setup, Safety & First Startup

Best Practices for Installing Rack UPS Systems in Data Centers

How to Install an Industrial UPS System: 10-Step Project Guide

Industrial UPS Systems: Applications, Benefits and Selection Guide




Get in touch with us
If you have any comments or good suggestions, please leave us a message; later our professional staff will contact you as soon as possible.
© 2026 ShanPu. All Rights Reserved.
Facebook
YouTube
SHANPU UPS